What Is the Anion Gap?
The anion gap is a laboratory calculation that helps clinicians think about acid-base balance and whether there may be an extra acid in the blood. It comes from routine electrolytes measured on regular chemistry panels, especially sodium and chloride, along with bicarbonate. Because the body must keep ion balance in the bloodstream, changes in these values can point to hidden problems in blood chemistry.
In simple terms, the anion gap is a way to look for a metabolic derangement. A high anion gap suggests more acid in the blood, while a normal anion gap can still occur in certain acid-base disorders but usually points to a different mechanism. This is why the anion gap is useful in lab interpretation: it helps identify the cause of systemic acidosis and guides more diagnostic testing.
One important detail is albumin. Since albumin is a protein with a negative charge, low albumin can make the anion gap appear reduced than it really is. That means the raw number is useful, but the clinical context matters. A complete interpretation considers the overall serum chemistry profile, including kidney status, glucose, bicarbonate, and other electrolytes.
The way an Anion Gap Calculator Operates
An Anion Gap Calculator is a fast tool that determines the gap from laboratory values. Most calculators use the same basic formula: sodium minus the sum of chloride and serum bicarbonate. Some versions also adjust for albumin, because albumin affects the reference baseline. The calculator does not diagnose the cause by itself, but it is a useful entry point for spotting anion gap elevation.
These tools are valuable because they convert numbers into clinical meaning. If bicarbonate is low, the calculator may show a gap that suggests acids are being added to the bloodstream. If chloride is relatively high and the gap stays normal, that may point more toward a normal anion gap pattern rather than a high-gap disorder. In other words, the calculator helps clinicians differentiate acid-base patterns before choosing on the next steps.
Common inputs include sodium, chloride, bicarbonate, and sometimes albumin. The result is then interpreted with the rest of the serum chemistry panel, symptoms, and other tests. Because the calculation is only one piece of the picture, it should be paired with blood gas testing and a full review of the patient’s history when there is concern for an acidotic state.
Can Diabetes Lead to a Elevated Anion Gap?
Indeed. Diabetes can lead to a high anion gap, especially when it progresses to diabetic ketoacidosis. Under these conditions, the body does not properly use glucose effectively because of insulin deficiency, so it begins breaking down fat. That process produces ketones, which are acidic. As ketones build up, they create metabolic acidosis and elevate the anion gap.
That is why diabetes is closely linked to ketoacidosis. The gap is not high because of glucose alone; it becomes high because the body is creating organic acids. The primary of these is beta-hydroxybutyrate, which is often the main ketone in diabetic ketoacidosis. As ketone production builds, bicarbonate is consumed buffering the acid, and the lab pattern shifts toward a elevated-gap metabolic acidosis.
It is also important to understand what diabetes does not automatically do. Many people with diabetes and high glucose do not have a high anion gap. The elevation happens when there is a real acid load, especially from ketones or another cause of acidosis. That is why the question is not simply “Does diabetes raise the anion gap?” but rather “Has diabetes caused an acid-base disorder that leads to anion gap elevation?”
DKA as the Main Cause
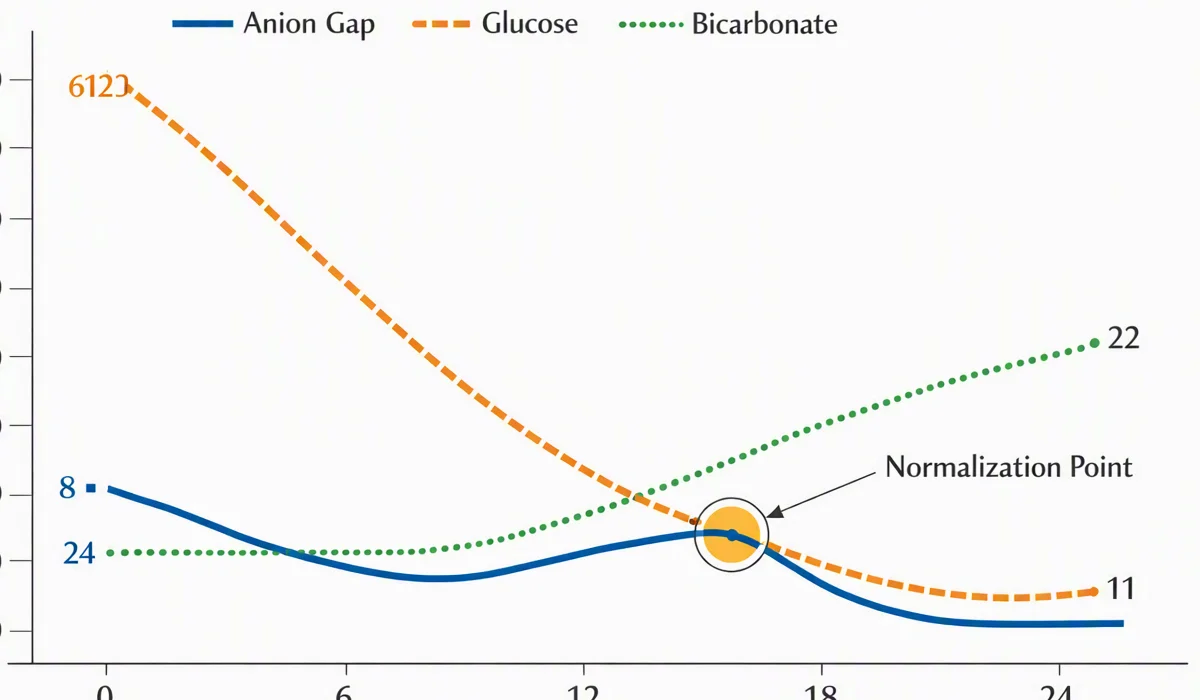
Diabetic ketoacidosis is the standard diabetes-related reason for a high anion gap. In this condition, insulin deficiency prevents normal glucose use, so the body turns to fat breakdown. Fat metabolism increases ketone production, especially beta-hydroxybutyrate, which contributes to metabolic acidosis.
As ketones build up, they function as organic acids and lower bicarbonate. The result is an acidotic state with a widened anion gap. This can happen fast and often comes with dehydration, vomiting, and marked glucose abnormalities. The presence of ketones in blood or urine supports the diagnosis, but blood beta-hydroxybutyrate is often the most reliable marker for the severity of ketoacidosis.
In simple terms, diabetic ketoacidosis is a immediately urgent condition because it signals a dangerous shift in metabolism. The high anion gap is not the disease itself; it is a clue that the body is failing to maintain normal acid-base balance.

Other Diabetes-Related Causes of Elevated Anion Gap
Although diabetic ketoacidosis is the primary explanation, other diabetes-related problems can also lead to an elevated anion gap. One example is lactic acidosis, which can occur when tissues do not get enough oxygen or when severe illness interferes with normal metabolism. Diabetes can contribute indirectly through poor perfusion, infection, or other complications.
Kidney failure is also an important concern. When renal function declines, the body cannot clear acids effectively, and metabolic waste products accumulate. This can produce a high anion gap even if ketones are not the primary issue. Diabetes is a common cause of chronic kidney disease, so the link matters in practical lab interpretation.
Hyperglycemia and dehydration often occur together in uncontrolled diabetes. While high blood sugar alone does not always raise the anion gap, severe dehydration can worsen circulation, impair kidney function, and contribute to lactic acidosis or ketoacidosis. So diabetes may create the conditions for a high-gap picture even when ketones are not the only factor.
What Indicators Point to a Severe High Anion Gap?
A worrying high anion gap often comes with clear clinical signs. One of the main is Kussmaul breathing, a deep rapid breathing pattern that shows the body’s attempt at respiratory compensation for metabolic acidosis. This pattern is particularly alarming when it appears with dehydration or confusion.
Other alerting symptoms include nausea, vomiting, abdominal pain, weakness, and signs of worsening illness. As the acid-base problem becomes worse, a person may develop altered mental status, ranging from confusion to lethargy. These symptoms suggest the body is struggling to maintain normal function during a significant metabolic derangement.
When symptoms are paired with diabetes, high glucose, and a high anion gap, the concern for ketoacidosis rises quickly. Because the condition can progress rapidly, treatment urgency matters. Any combination of deep breathing, vomiting, dehydration, and confusion should be taken with urgency.
In What Way Doctors Confirm the Cause
To confirm the cause of a high anion gap, physicians combine several tests instead of relying on one result. A basic metabolic panel is often the starting point because it shows sodium, chloride, bicarbonate, and glucose. These values help determine the pattern and judge the severity of the acid-base disorder.
A blood gas is then obtained to assess pH and the degree of acidosis. It helps determine whether the body is in a true acidotic state and whether there is adequate respiratory compensation. Because the anion gap is only one part of the picture, a blood gas adds key context for diagnosing systemic acidosis.
Doctors also check glucose and perform a ketone test, especially if diabetes is known or suspected. Blood ketone testing is often preferred because it can detect beta-hydroxybutyrate more directly. Together, the glucose level, ketones, and basic metabolic panel help distinguish diabetic ketoacidosis from other causes such as lactic acidosis or kidney failure.
Albumin may also be reviewed to interpret the gap correctly. A low albumin level can mask an elevated gap, so clinicians may adjust the calculation or interpret the result carefully. This is where thoughtful lab interpretation and diagnostic testing work together.
When a High Anion Gap Is an Emergency
A high anion gap becomes an urgent situation when it reflects marked acidosis, rapidly worsening symptoms, or suspected diabetic ketoacidosis. This is the point where emergency care is necessary because the body may be unable to compensate any longer. A dangerous acid load can affect the way you breathe, blood flow, and brain function.
Common emergency treatments include fluid replacement and insulin therapy, particularly when diabetic ketoacidosis is the cause. Fluids help correct dehydration and improve perfusion, while insulin reduces blood sugar and stops ketone production. As ketones fall and bicarbonate returns, the anion gap can begin to close.
Severe acidosis is not something to watch at home. A person with Kussmaul breathing, vomiting, confusion, or very high glucose needs urgent medical evaluation. The goal is not just to lower the number on the calculator but to treat the metabolic emergency before it causes greater complications.
FAQ On Diabetes and High Anion Gap
Does diabetes cause a high anion gap?
Absolutely. Diabetes can lead to a high anion gap, primarily through diabetic ketoacidosis. In that setting, insulin deficiency promotes ketones, especially beta-hydroxybutyrate, which create metabolic acidosis and increase the anion gap.
Will diabetic ketoacidosis always lead to a high anion gap?
Most of the time, yes, because diabetic ketoacidosis creates acid from ketones and lowers serum bicarbonate. However, lab patterns can change depending on timing, treatment, and other factors, so clinicians look at blood gas results, ketone test findings, and the basic metabolic panel together.
Can high blood sugar raise the anion gap without ketoacidosis?
High blood sugar alone does not necessarily elevate the anion gap. The gap usually goes up when hyperglycemia is part of a larger metabolic acidosis, such as ketoacidosis, lactic acidosis, or kidney failure. That is why glucose must be assessed with electrolytes, ketones, and clinical signs.
Which is the normal anion gap range?
The anion gap normal range depends on the laboratory and https://anion-gap-calculation.com/calculators/anion-gap.html the formula used, including whether albumin is considered. Many labs use a range that is roughly around 8 to 12 mEq/L, but reference intervals vary. The most important step is to compare the result with the specific lab’s reference range.
When should a high anion gap be considered an emergency?
A high anion gap should be considered an emergency when it is paired with severe acidosis, deep or rapid breathing, vomiting, confusion, dehydration, or suspected diabetic ketoacidosis. In those situations, emergency care is needed right away because the cause may require fluid replacement, insulin therapy, and close monitoring.